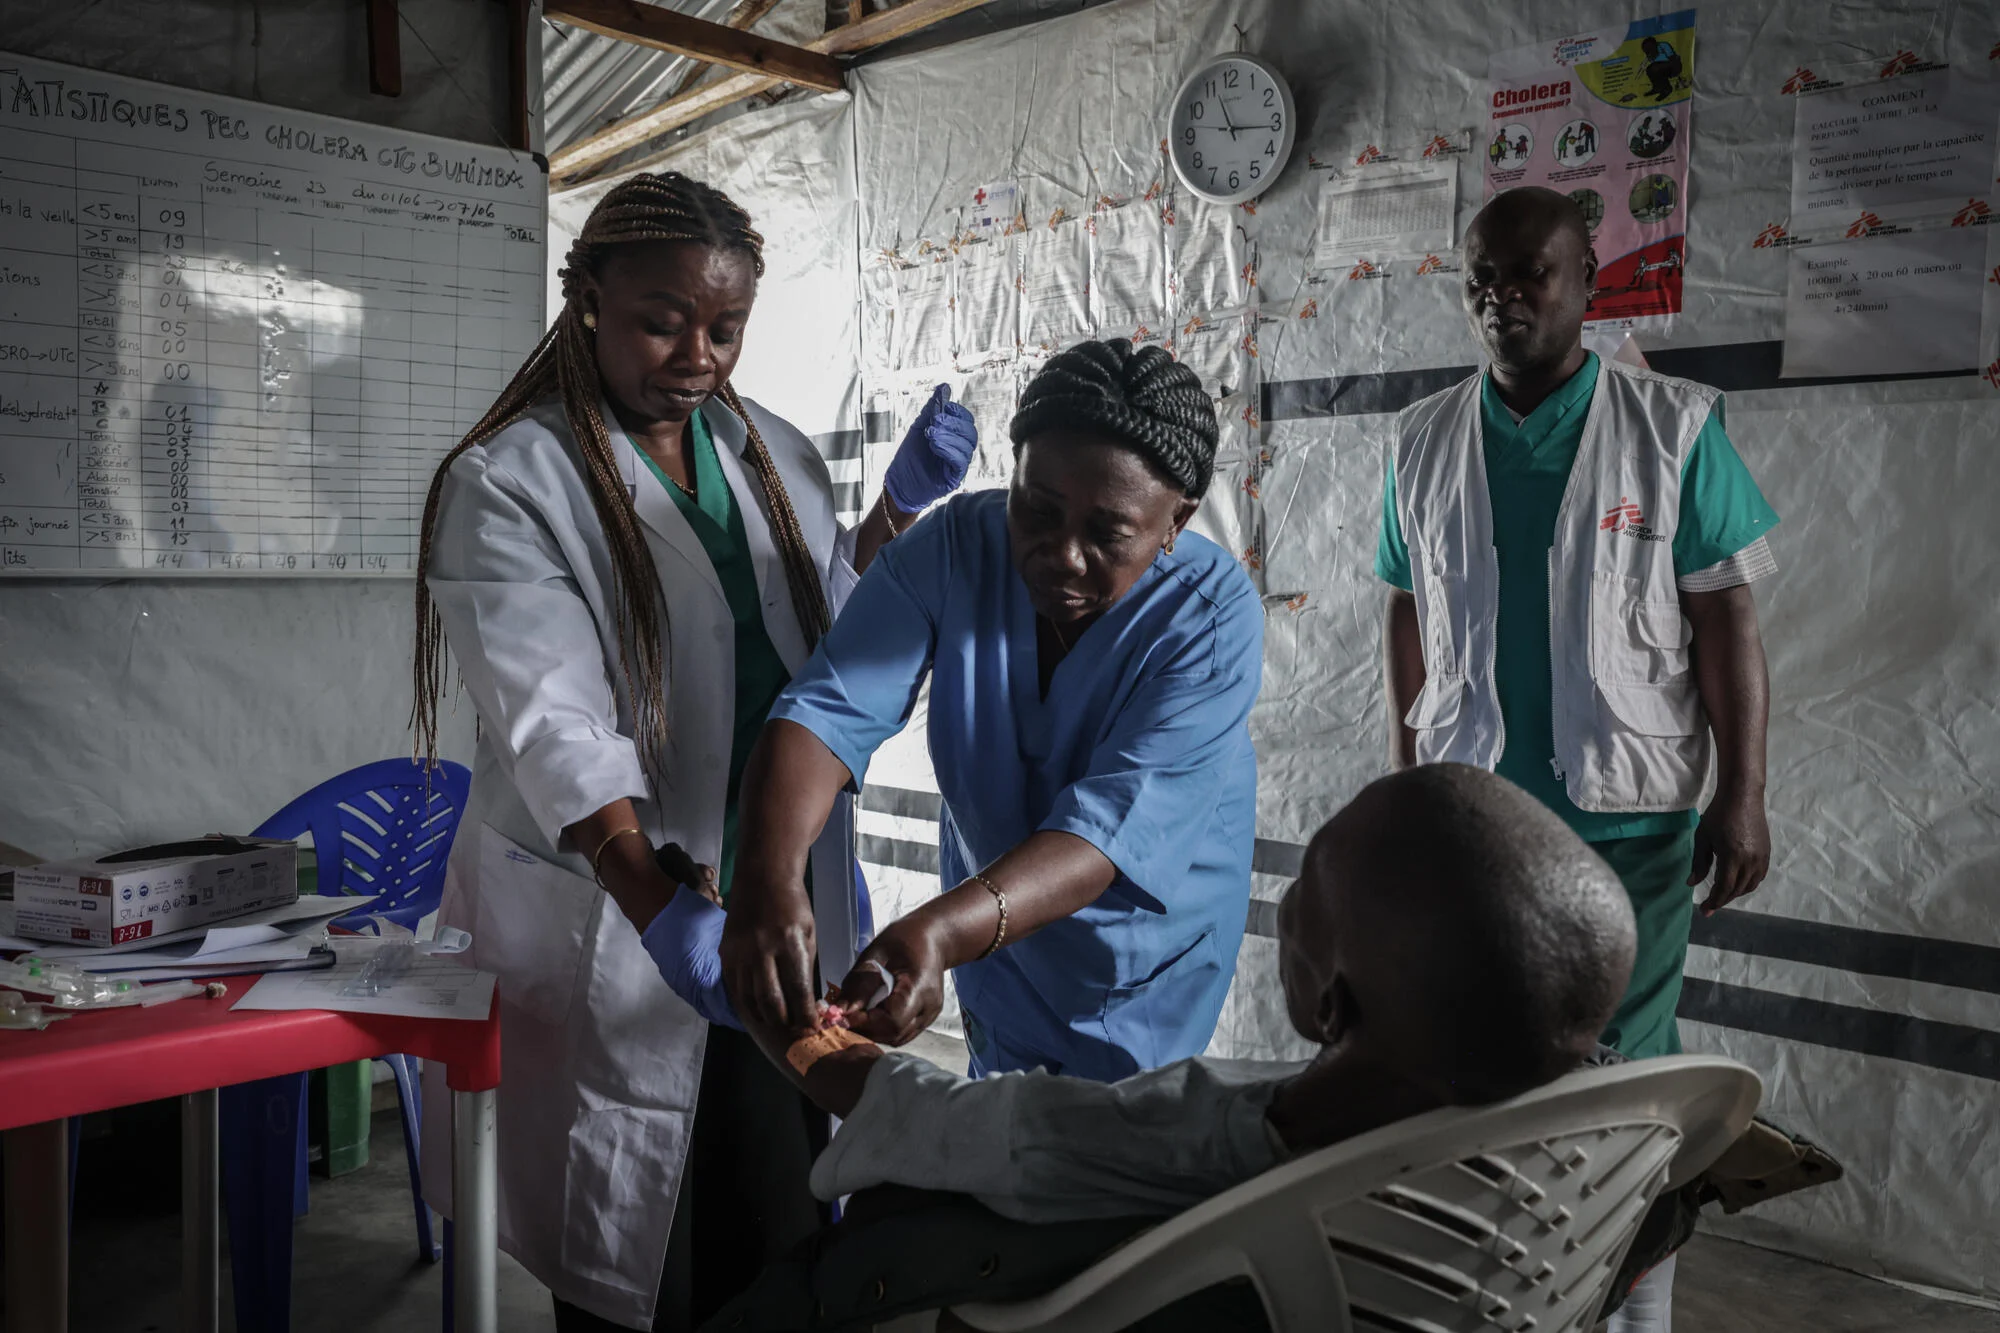
Ebola is now in Kenya.
As of 18 October, the Ministry of Health had confirmed eight cases of the Bundibugyo virus, Reuters reported.
One person has died.
Three of those infected are health workers who treated the first patient, a Kenyan man who had travelled from the Democratic Republic of Congo (DRC) through Uganda, on 3 and 4 October.
In the DRC, the virus had caused 4,478 deaths among 9,277 confirmed cases since May, as of 15 October, according to the European Centre for Disease Prevention and Control (ECDC).
Kenya prepared.
It tightened screening at airports and borders and opened an emergency hotline. It trained 4,971 health workers and named five hospitals holding 244 beds.
By 17 October, 128 of 130 listed contacts were in quarantine.
These measures answer the Ebola question.
But when Ebola passes, will Kenya be left with a specialised hospital, or still with a plan, for the next infectious disease?
Five months of preparation
Kenya has been on high alert since May, when outbreaks were declared in the DRC and Uganda, according to the World Health Organization (WHO).
By 6 October, the ministry said, 652,584 travellers had been screened at entry points and 267 suspected samples tested across five laboratories.
Isolation units in 27 high-risk counties had been identified and assessed, WHO said, and Kenya's Ebola preparedness score, which tracks surveillance, laboratory testing, isolation and treatment facilities and trained response teams, rose from 66% in May to 82% in July.
A toll-free hotline runs on 719.
In July, Mombasa County, with Médecins Sans Frontières, opened an Ebola training centre at Port Reitz Hospital, which can also serve as an emergency isolation unit, the Nation reported.
Testing is where the record is strongest.
A sample taken from the first patient on 5 October tested positive at both the National Virology Reference Laboratory and the Kenya Medical Research Institute (KEMRI) laboratory the same day, WHO reported.
The Kenya National Public Health Institute hosts four national reference laboratories, a high-containment laboratory and two mobile laboratories, the ministry said on 4 August.
Kenya's first case was announced on 6 October and its second on 14 October.
Every case confirmed since has been someone already in quarantine, meaning kept apart and checked daily: relatives of the first patient, the three health workers who treated him and, on 18 October, a 49-year-old patient attendant who cleaned the first patient's utensils and linens.
Dr Patrick Amoth, the ministry's Director-General for Health, said the man is not a health worker and was probably exposed to the first patient, Reuters reported. He developed symptoms on 17 October and tested positive the next day.
"This is the response working as designed," the ministry said of the second case.
Of about 130 contacts of the first patient, 128 were in quarantine, which is above the global benchmark of 85% for breaking chains of transmission.
WHO's regional director for Africa, Dr Mohamed Janabi, said Kenya had put important outbreak control measures in place.
On 7 October, Health Cabinet Secretary Aden Duale named five hospitals for Ebola patients: Nairobi Hospital; Moi Teaching and Referral Hospital in Eldoret, in the Rift Valley; the National Police Service Hospital in Nairobi; Kenyatta National Hospital, the largest public referral hospital, also in Nairobi; and Port Reitz Hospital in Mombasa.
How the first patient passed airport screening has drawn questions from observers, Al Jazeera reported.
WHO said he arrived on 3 October and was taken by a relative directly to Nairobi Hospital, where he was isolated. He died on 5 October.
That is detection and containment, and the evidence for both is good. The harder test is the ward.
A bed is not a team
The 244 beds are the ministry's own count: 133 at Nairobi Hospital, 50 at Moi, 49 at the National Police Service Hospital, eight at Kenyatta and four at Port Reitz.
A designated bed is one that has been set aside, and the list mixes different kinds. Moi's 50 are 20 isolation beds plus 30 surge beds, the Nation reported.
The National Police Service Hospital's 49 are beds available for activation as surge capacity. About 45 of Nairobi Hospital's 133 are high-dependency and intensive care beds.
Consider the national unit at Kenyatta.
It has eight beds, five of them intensive care.
It was set up in 2014 and also handles tuberculosis, measles and chickenpox, and the Nation reported in June that if it fills with other infectious patients it cannot admit Ebola cases.
On 4 August the ministry said the unit had managed 58 suspected Ebola cases, all negative, with 38 health workers specially trained in highly infectious diseases.
Prof Shem Otoi, an infectious disease modelling expert, told the Nation that only four doctors and about 20 nurses could handle critically ill Ebola patients there.
He added that training is different from protecting frontline workers.
The ministry has not said how many staff across all five hospitals are trained and ready to care for critically ill patients, or how county hospitals, where most patients first walk in, recognise, isolate and refer a suspected case.
The Nation reported in July that a response report listed unresolved gaps in holding, temporary and permanent isolation facilities, and that the analysis of the full shortfall was still under way more than seven weeks into the response.
Where Ebola infects the people who treat it
That matters because of where infections have happened before.
When Ebola reached Lagos in 2014 in a traveller from Liberia, he was taken to a private hospital and initially treated for presumed malaria.
Twelve of Nigeria's 20 cases were exposed in two health facilities, the US Centers for Disease Control and Prevention (CDC) reported.
It also said the first isolation ward there was delayed because too few health workers were willing to staff it, for lack of information and training.
By mid-August 2015, WHO had counted 880 confirmed health-worker infections in Guinea, Liberia and Sierra Leone, and 512 deaths.
Kenya's first patient fits the pattern. He had been ill for about a month, and WHO said he probably caught the virus in a health facility or in the community while seeking care for another ailment.
WHO also notes that transmission is amplified in health facilities when infection control is inadequate.
The three Kenyan health workers attended him on 3 and 4 October, before the case was announced on 6 October, and the ministry says they were in quarantine from 9 October. Their exposure came before the diagnosis.
The ministry has not said how they were infected, and an infected health worker is not proof of a careless one.
The eighth case, the patient attendant, is not a health worker, the ministry says, but he was also probably exposed to the first patient.
A ward for confirmed patients alone would have come too late for them.
Whatever Kenya builds has to reach the hospital where the next feverish patient walks in.
What a permanent team changes
Once a patient is confirmed, the quality of care matters.
WHO says no vaccine or specific treatment is approved for Bundibugyo, which leaves supportive care.
Of 27 Ebola patients treated at 15 hospitals in nine countries in the United States and Europe in 2014 and 2015, five died, or 18.5%.
Mortality in West African treatment units ranged from 37% to 74%, according to the New England Journal of Medicine report led by Dr Timothy Uyeki.
The authors said their experience suggests early supportive care may reduce deaths.
The authors' patients were a different group from West Africa's, mostly evacuated from or infected there, and the study had no comparison group, so it shows what is possible rather than proving a cause.
WHO said on 8 October that rapid recognition, testing and optimised supportive care can reduce deaths.
A permanent team also has work between outbreaks. As of 6 September, Kenya had recorded 1,298 confirmed mpox cases and 19 deaths across 40 counties, the ministry said.
That is infectious disease work in a year without Ebola, and a hospital with a standing team would have it to do. One that waits for the next Ebola case would stand idle.
What the United States built after Dallas
In September 2014, a man back from Liberia went to a Dallas hospital with a fever and was sent home. He returned days later and died on 8 October.